
Articles, videos about Tongkat Ali
Tuberculosis
Tuberculosis is a very slow disease. Mycobacterium tuberculosis only divides (multiplies) about once in 18 to 24 hours, if at all.
By comparison, in human hosts, Streptococcus pneumoniae, the most common cause of bacterial pneumonia, divides every 1 to 2 hours.
Conventional treatment by chemotherapy is also slow. It relies on 4 first-line drugs, Rifampin (Rifampicin), Isoniazid,
Pyrazinamide, and Ethambutol.
As a standard regimen, Rifampin and Isoniazid should be taken for 6 months, with Pyrazinamide and Ethambutol
added in the first 2 months. Side effects are substantial.
"Most current TB regimens consist of six to nine months of daily doses of four drugs that are highly toxic to patients."
"Prolonged treatments with severe side effects reduce patients' physical and mental endurance during the course of treatment."
Mycobacterium tuberculosis can evade eradication by the immune system, as well as by anti-tuberculosis chemotherapy, in a variety of ways.
"Mycobacterium tuberculosis (MTB) is an intracellular parasite that mainly attacks macrophages and inhibits their apoptosis."
"We demonstrate that M. tb suppresses T-lymphocyte responses..."
"The outcome of M. tuberculosis infection is often a state of equilibrium characterized by immunological control and bacterial persistence."
Even if tuberculosis is treated with a 6-month chemotherapy, the Mycobacterium tuberculosis is not eradicated in a human host.
Because drugs target metabolic processes of the bacteria, a certain population
of bacteria in a dormant state (with paused metabolisms) cannot be destroyed by the drugs. Such bacteria are called persisters.
There is a definite chance that, at a time the host immune system is weakened, the disease will come back in its active form.
"The recurrence incidence was 8.3% and in 85.9% of these patients, it occurred in the time interval of 1-5 years after successful treatment."
A 2012 study on persisters prominently quoted Walsh McDermott: "When one realizes that, even though the bacilli vanish and there is … truly latent
infection, the bacilli are, nevertheless, still there … drug susceptible, I think you will agree with me that it shows that ‘you can't win.’"
Conventional anti-tuberculosis drugs work on highly sophisticated pathways. "Tuberculosis drugs target various aspects of Mycobacterium tuberculosis
biology, including inhibition of cell wall synthesis, protein synthesis, or nucleic acid synthesis."
The sophisticated pathways by which anti-tuberculosis chemotherapy target Mycobacterium tuberculosis are a testament proving the
ingenuity of the pharmaceutical industry. However, the fact remains that all these interventions are toxic not only to the pathogen
but also the human host.
The toxicity of tuberculosis drugs
The four first-line drugs in tuberculosis chemotherapy are: Rifampin (Rifampicin), Isoniazid, Pyrazinamide, and Ethambutol.
Here first some rather harmless patient reviews.
For Rifampin:
For Isoniazid:
Scientific research into side effects is more scary.
The combined chemotherapy is toxic to the kidneys.
"The standard anti-tuberculosis (TB) regimen occasionally causes acute kidney injury (AKI). The major etiology is rifampicin-induced
acute interstitial nephritis... Among 1,430 patients with active TB, 15 (1.01%) developed AKI...
The renal function was normalized in 12 patients (80.0%) after restarting anti-TB treatment without rifampicin (n=12) or isoniazid (n=1).
Two patients died due to severe renal failure after restarting rifampicin."
A drug (toxin) that comes with a definite risk of acute kidney injury is likely to be detrimental to kidney function even when acute kidney
injury does not occur.
"TB patients had a significantly higher risk of developing CKD [Chronic Kidney Disease] than the general population."
Standard tuberculosis therapy is also toxic to the liver.
"Drug-induced liver injury (DILI) is a common complication of tuberculosis treatment... A total of 58 of 1928 (3.0%) patients met the criteria for
DILI defined in this analysis."
Second-line aminoglycoside tuberculosis drugs are toxic to human hearing.
"Sixty four patients were put on second line aminoglycoside anti-TB drugs. These were divided into three groups: group I, 34 patients using amikacin,
group II, 26 patients using kanamycin and group III, 4 patients using capreomycin. Of these, 18.75% of the patients developed
sensorineural hearing loss involving higher frequencies while 6.25% had involvement of speech frequencies also.
All patients were seen again approximately one year after aminoglycoside discontinuation and all
hearing losses were permanent with no threshold improvement."
"A total of 42 Patients undergoing multidrug resistant tuberculosis treatment participated in the study... The study found 45.23% participants with some
degree of hearing loss consequent to multidrug resistant tuberculosis treatment. Around 9.5% of the total participants developed potential
disabling hearing loss."
Ethambutol, a first-line tuberculosis drug, is toxic to the optic nerve. The common dosage is 15mg/kg bodyweight. Blindness can occur
even at that dosage. At dosages of 100mg/kg bodyweight, blindness is almost a certainty. There is no space in this article to
deal with all side effects of this drug, but here is a link for more detail:
"We describe a 43-year-old man who developed signs and symptoms of bilateral optic neuropathy during treatment with ethambutol.
Ethambutol was initiated at a dosage of 15 mg/kg per day. Three months later, the patient had lower extremity neuropathy,
and 2 weeks after that he developed a rapidly progressive, severe decrease in vision... Visual acuity testing before initiation of treatment showed
20/20 vision in both eyes and normal color vision. Ophthalmologic examination [after ethambutol treatment] revealed a best corrected visual
acuity of 20/200 with the right eye and counting fingers at 4 feet with the left eye... Manifestations of toxicity can
occur as late as 12 months after initiation of therapy."
There are hundreds of potential side effects for the combined tuberculosis drugs. Acute kidney injury may only occur in 1 percent,
tragic enough. But the risks add up, with possible permanent blindness and deafness standing out, and it is very unlikely indeed,
especially for older patients, that they get through tuberculosis chemotherapy unscathed.
"Side-effects such as hepatitis [liver inflammation], dyspepsia [stomach pain that often gets worse with eating], exanthema [widespread skin rash]
and arthralgia [joint pain] were responsible for termination of therapy in up to 23% of patients during the intensive phase... The side-effects
profile of TB chemotherapy is magnified in... those being treated with second-line drugs for multidrug-resistant TB, during which as
many as 86% of patients may develop medication side-effects."
Are there less toxic alternatives?
Practitioners of orthomolecular medicine believe that megadoses of vitamin C can keep any infection in check, and tuberculosis
is not excluded from the claim.
There also is a range of scientific studies that point to benefits in the treatment of tuberculosis by adding vitamin C to conventional
chemotherapy, though no study was published as of now that would have examined the effectiveness of vitamin C megadoses alone, or compared the
use of megadoses of vitamin C-only with conventional tuberculosis chemotherapy. Such trials are also unlikely to come along any time soon.
Big pharma won't provide funding for vitamin C studies, as positive results would certainly be negative for their bottom line.
While the benefits of megadoses of vitamin C in the treatment of tuberculosis have not been scientifically proven, the bias of the
medical establishment against vitamin C has.
"Bias against Vitamin C in Mainstream Medicine: Examples from Trials of Vitamin C for Infections... In mainstream medicine, the views on
vitamin C and infections have been determined by eminence-based medicine rather than evidence-based medicine."
In order to convince the medical establishment on the validity of megadoses of vitamin C in the treatment of tuberculosis,
sensational case reports on miraculous disease reversals won't be enough. To start with, explanations will be required on
how vitamin C is supposed to work as a treatment for tuberculosis.
The strongest candidate for such an explanation is how vitamin C can drive Fenton reactions to destroy Mycobacterium tuberculosis.
See below how AI summarizes this well-established process:
https://tongkatali.org/tuberculosis-
Below quotes from scientific articles on vitamin C and tuberculosis:
"Mycobacterium tuberculosis is extraordinarily sensitive to killing by a vitamin C-induced Fenton reaction...
The bactericidal activity of vitamin C against M. tuberculosis is dependent on high ferrous ion levels and reactive oxygen species production,
and causes a pleiotropic effect affecting several biological processes."
The original location of the video is on Youtube.
"Like all human pathogens, Mtb requires iron for growth and virulence... Mtb iron uptake is a complex process,
requiring biosynthesis and subsequent export of Mtb siderophores, followed by ferric iron scavenging and ferric-siderophore
import into Mtb... The battle for iron between the human host and bacteria has evolved into a sophisticated cat and mouse game,
where bacteria have developed complex pathways to steal iron from host proteins, and to circumvent this, humans have evolved
proteins to neutralize bacterial iron-scavenging pathways."
It is a lesser-known function of the immune system to limit iron availability.
"Given the absolute requirement for iron by virtually all human pathogens, an important facet of the innate
immune system is to limit iron availability to invading microbes in a process termed nutritional immunity...
Iron limitation as an innate immune defense... Hemoglobin in senescent erythrocytes is meticulously recycled by macrophages."
Iron limitation is an innate immune defense. In chronic infections like tuberculosis, iron limitation leads to anemia of inflammation.
Taking iron supplements to alleviate the anemia often seen in tuberculosis patients, is probably not a wise strategy.
"Increase in host Fe levels promotes Mtb growth and tuberculosis (TB) pathogenesis, while Fe-supplementation to latently infected,
asymptomatic individuals is a significant risk factor for disease reactivation."
Macrophages are extraordinarily rich in iron.
"Macrophages play a crucial role in iron trafficking, as they recycle the large quantity of iron obtained by hemoglobin degradation.
They also seem particularly adapted to handle and store amounts of iron that would be toxic to other cell types."
Mind you, "Mycobacterium tuberculosis... mainly attacks macrophages and inhibits their apoptosis."
As macrophages infected by Mycobacterium tuberculosis are rich in ferric ions, it may make sense to see them as suitable targets
for vitamin C-induced Fenton reactions.
Other alternatives to toxic chemotherapy?
In the first half of the 20th century, when chemotherapy was not yet discovered, tuberculosis treatment relied on
supportive treatment, nutrition, bedrest, fresh air, and heliotherapy. From Nature in 1922: "The treatment of disease by sunlight is the
newest of old things. It was systematically practiced by Hippocrates... The first clinic for the heliotherapy of surgical tuberculosis
was opened by Dr. A. Rollier in Leysin in 1903."
"In Europe, the first sanatorium was founded in 1854 by Hermann Brehmer in Germany, in Goebersdorf in Silesia, a village on the border
between Poland and the Czech Republic... His method of treatment spread throughout Germany, France and Switzerland, especially in the
egion of Davos, in the Engadin Valley, where the first high-altitude sanatoria were opened for paying patients...
The new sanatoria were designed in such a way that patients could stay in single rooms or rooms with a few beds,
which usually gave onto large terraces where inmates could take so-called “sun baths”.
The buildings were surrounded by spacious meadows and tree-lined gardens, where guests could go for long healthy walks.
Patients stayed in the institution for very long periods – from a minimum of six months to seven, eight or even 16 years."
"An estimated 40% of people who developed TB in 2021 were not diagnosed or treated. Pre-chemotherapy era data are a rich resource on
survival of people with untreated TB... We found 12 studies with TB-specific mortality data. Ten-year survival was 69% in North America and
36% in Europe. Only 38% of non-sanitorium individuals survived to 10 years compared to 69% of sanitoria/hospitalized patients...
Geographically, people in North American studies experienced better outcomes than those in Europe.
This may be because North America was more shielded from the worst effects of the two world wars in the early twentieth century than Europe."
And after successful chemotherapy:
"The median of survival time after successful treatment was 10.5 years and survival probability for 11 years after successful treatment was 70%...
This study showed that positive smear pulmonary tuberculosis even after successful treatment has an adverse effect on the patients’
survival and leads to a decrease in their survival rate in the long run."
"We used local health authority records from 3 US sites to identify 3853 persons who completed adequate treatment of TB and
7282 individuals diagnosed with latent TB infection 1993 to 2002... We found more all-cause deaths (20.7% vs 3.1%) among posttreatment
TB patients than among the comparison group... Fully treated TB is still associated with substantial mortality risk.
Cure as currently understood may be insufficient protection against TB-associated mortality in the years after treatment."
"Based on a retrospective cohort study, information of 2,299 TB patients that had been referred to and treated at the NRITLD
[National Research Institute of Tuberculosis and Lung Disease], Masih Daneshvari Hospital [Teheran, Iran], from 2005 to 2015, was collected...
This study was done on 2,299 patients with treated pulmonary TB; 770 patients (33.49%) expired and 134 patients (5.83%) had disease relapse."
In the Iranian study, the ten-year survival rate of tuberculosis patients undergoing chemotherapy was 66.51%. That is even worse
than the ten-year survival rate of 69% in North America in the pre-chemotherapy era.
Tuberculosis and high altitude
Living at high altitudes slows tuberculosis progression, and improves the odds of self-cure. This was observed in the pre-chemotherapy era,
and it has been confirmed in recent scientific research. The following is from a 2013 study.
"Antimycobacterial immunity was assayed in 15 healthy adults residing at low altitude before and after they ascended to 3400 meters; and in 47
long-term high-altitude residents. Antimycobacterial immunity was assessed as the extent to which participants’ whole blood supported or
restricted growth of genetically modified luminescent Bacille Calmette-Guérin (BCG) mycobacteria during 96 hours incubation... At low altitude,
mycobacteria grew in blood 25-times more than negative-control plasma whereas ascent to high altitude was associated with restriction (p=0.01) of
mycobacterial growth to be only 6-times more than in plasma. There was no evidence of differences in antimycobacterial immunity at high altitude
between people who had recently ascended to high altitude versus long-term high-altitude residents."
The above matches scientific research that has been conducted in the pre-chemotherapy era.
"In 1925, for example, the experiments of Novy and Soule on the 'Respiration of the Tubercle Bacillus' showed that higher than usual ambient oxygen
concentrations... enhanced bacillary growth... by contrast, exposure to lower than normal oxygen concentrations showed 'for the first time'
that growth 'decreased progressively as the [oxygen] tension was lowered'; 2 years later, the experiments of Corper, Lurie, and Uyei came to
nearly similar conclusions about the effects of low oxygen tensions. Then, in 1939, Kempner determined that the rate of oxygen utilization of
cultured tubercle bacilli decreased in curvilinear fashion as the oxygen percentage of exposed bacilli was reduced."
In the late 19th and early 20th century, it was common knowledge that higher altitudes afforded a window of opportunity against tuberculosis.
"The introduction of the sanatorium cure provided the first real step against TB. Hermann Brehmer, a Silesian botany student suffering from TB,
was instructed by his doctor to seek out a healthier climate. He traveled to the Himalayan Mountains where he could pursue his botanical
studies while trying to rid himself of the disease. He returned home cured and began to study medicine. In 1854, he presented his doctoral
dissertation bearing the auspicious title, Tuberculosis is a Curable Disease. In the same year, he built an institution in Gorbersdorf where,
in the midst of fir trees, and with good nutrition, patients were exposed on their balconies to continuous fresh air. This setup became the
blueprint for the subsequent development of sanatoria, a powerful weapon in the battle against an insidious opponent."
Tuberculosis and bed rest
Up until the mid-20th century, bed rest was the most promising treatment for tuberculosis.
Patients, especially those from families of sufficient wealth, stayed for months or years at sanatoria where they passed their days in
tranquil natural environments, hanging around on sofas on balconies, or, if febrile, lying in bed.
"It wasn't until the development of the Sanatorium in which careful observations were made... that the rest cure came into the foreground
as the most important factor in combating the disease. “Rest” is the most important single factor in the treatment of pulmonary
tuberculosis. - Chest Journal, January 1942, Rest in Treatment of Tuberculosis by Savere Madonna, MD
But just when discoveries were made on why bed rest sometimes was successful, and how it could be optimized, along came the discovery
of streptomycin and other agents of chemotherapy which were way more economical than sanatoria and more reliable in treating the disease,
albeit at the cost of substantial systemic side effects.
The proposed optimization of bed rest (in which mainstream medicine was no longer interested) was based on a better understanding of lung physiology.
"The purpose of this review is to re-examine the physiologic evidence pertaining to these treatments [bed rest, pneumothorax] and to emphasize why we
should have listened to one man, William (Bill) Dock, who told us all long ago how bed rest should be performed and why certain types of
collapse might be helpful.
It is an established observation in the diagnosis of pulmonary tuberculosis that the bacilli have a preference for the upper one third, and even
the apices of the lungs.
"What could possibly explain these... preferences?... The answer was finally provided by Bill Dock... who came up with a very simple
explanation...: gravity, which has important effects on both the distribution of inspired air and the distribution of pulmonary arterial
blood flow within the lungs."
Mycobacterium tuberculosis is an obligate aerobe. It needs oxygen to thrive, the more the better.
The availability of oxygen to the bacilli isn't uniform in the normal human lungs. In the upright position, in which people find themselves for
most of the day when standing, walking, or sitting, gravity causes the bases of the lungs to receive the most blood supply, and this is
where most gas exchange takes place.
Normal tidal breathing involves only 1 to 2 liters of air per breath, while the full lungs volume of the average
person is 5 to 6 liters.
When only 1 to 2 liters of air are used in gas exchange in about one third of the lungs, the remaining capacities of the lungs are not empty.
They also contain air, mostly oxygen-rich.
One such part of each lung which is filled with air that participates little in gas exchange is the upper lobe, especially the apex.
"Very little of the total oxygen uptake occurs at the apex, principally because the blood flow there is very low... Note that the base of the
lung has most of the blood flow, but the PO2 [oxygen tension, oxygen pressure] and oxygen concentration of the end-capillary blood are lowest
there. As a result, the effluent pulmonary venous blood (which becomes the systemic arterial blood) is loaded with moderately
oxygenated blood from the base."
In people who go about their lives in a normal manner, with the lungs upright for most of the day, the upper lobes present an ideal
environment for the bacilli. They contain oxygen-rich air which, because of the effects of gravity on blood flow in the pulmonary circulation,
is largely unaffected by the fluctuations of gas exchange.
And the forces of gravity in the erect human host work in favor of the bacilli not only because of stable oxygen-rich air pockets,
but also by shielding the bacilli from a full-blown attack by the host immune system. Not only the flow of blood to the apices of the
lungs is hampered in the upright position, but even more so the flow of lymph.
All of this can be reversed by positional intervention. When a human host is lying flat on his or her back, then, all of a sudden,
the apices of the lungs are no longer a haven of oxygen-rich air with little gas exchange. On the contrary, the apices are now, because of
gravity, an area of intense blood flow and gas exchange. Furthermore, also because of gravity, the immune system, via lymph, has a new tactical
advantage over the pathogen.
Bed rest, it must be noted, is most effective if a person lies flat on his back. But many by-and-large healthy people, and most people
confined to hospital beds for any kind of disease, do not lie flat. They pop up their upper torsos with pillows, or adjust their
hospital beds to up to 45 degree. This may be fine for many diseases, and even beneficial for GERD (gastroesophageal reflux disease)
but negates the desired end points in the case of tuberculosis.
As many historical images of patients in sanatoria prove, bed rest was often done wrong, with upper torsos elevated.
This surely was comfortable, not only for the human hosts but also for the bacilli.
An excellent summary on the importance of body position was provided by Scott Welker MD at an unlikely Internet
location, Quora:
"Rest therapy for TB works mainly because of the position of the patient when they are at rest. Partly because of reduced stress on the immune
system and cleaner air also, but mainly it was that laying down deprived the TB of oxygen.
"The Mycobacterium tuberculosis organism is a strict aerobe, and it thrives in environments with excess oxygen. The opposite is also true -
deprive it of oxygen, and it fares poorly.
"To explain this I first need to explain pulmonary physiology. Obviously we have a large pulmonary reserve. That’s why you can breathe
hard enough to run, or work hard, of row a boat. Your lungs can support much greater exertion than you are experiencing right now.
A healthy adult can even get by after an entire lung is removed!
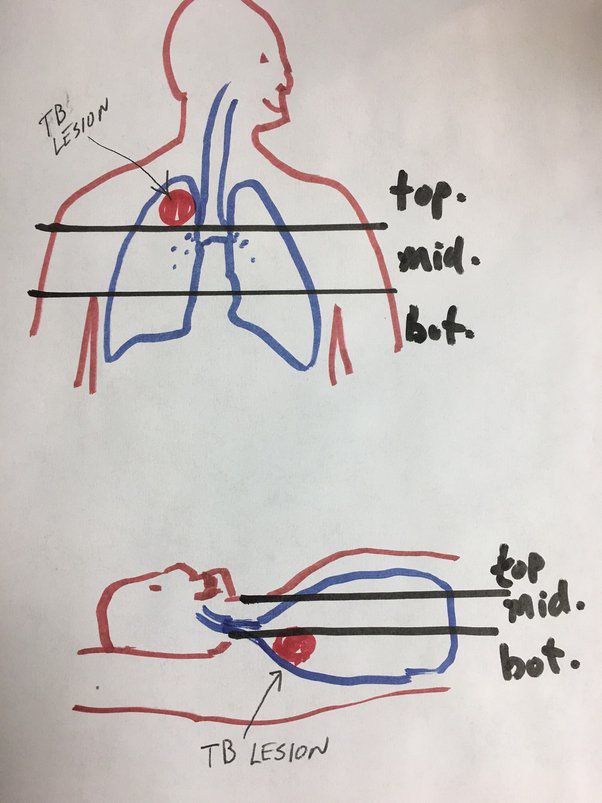
"At rest, we only need about 1/3 of the capacity of our lungs. Oxygen exchange takes place mainly in the middle third, as the bottom third of
the lungs are congested by blood flow and not well aerated. The top third is well aerated, but only gets enough blood flow for the lung itself;
very little blood flows into the oxygen-exchange vessels. So that’s one of the reasons TB favors the upper 1/3 of the lung; there’s tons of
oxygen there that’s not being used. We inhale it, then exhale it without absorbing it... Here’s a cartoon I drew to illustrate this:
"So, when you lie in a bed, you’re still only using the middle 1/3 of your lung for oxygen exchange. same situation as when you’re standing,
but now your lung is horizontal. The top 1/3 faces the ceiling, and the bottom 1/3 faces the floor. The slices of the sandwich still go
90 degrees to up and down, but some or all of the M. tuberculosis colony in the chest is either struggling with less oxygen
(which exchanged in your lungs’ middle 1/3), or getting no oxygen at all (it’s submerged in your lungs’ bottom 1/3).
"In his brilliant 1934 Textbook of Medicine, Dr. Russel B. Cecil pointed this out. Even though we hadn’t figured out the 'lung in thirds' model
I speak of above, because we lacked the equipment to take blood pressures in the pulmonary veins and do nuclear medicine perfusion scans,
Cecil deduced the truth of this. He said 'rest is the only treatment which has proved entirely successful.' He went on to point out that
patients who had disease on one side of their chest only (which we could see on X-rays and bronchoscopy), were better served to lie with
their diseased lung down.
"He even forbid patients from 'sitting up in a chair or reclining in a chaise-lounge.' ... So there you have it - rest worked for TB because
it deprived the organism of oxygen.
Tuberculosis in the elderly population
Tuberculosis in the elderly population often presents fewer symptoms.
"Symptoms of active TB are nonspecific and less pronounced in the elderly."
"Difficulties in diagnosis tuberculosis in older adults has been assessed in a meta-analysis of studies focusing on tuberculosis
in older adults, which found that common symptoms used to identify tuberculosis such as dyspnoea [shortness of breath], haemoptysis [coughing blood]
and fever are less prominent in older than in younger adults."
“Classical symptoms of TB (cough, haemoptysis [coughing blood], fever, nights sweats and weight loss) were less common among older patients with
pulmonary TB (PTB)... For those with PTB, chest radiography findings showed that cavitation and lymphadenopathy were more common among younger
patients. Conclusions: Older patients aged ?65 years with TB had fewer “classical” clinical and radiological presentations of TB, which
may explain longer times to starting treatment from symptom onset compared with younger patients aged <65 years... TB in the elderly presents
with fewer of the classical symptoms of TB, less specific radiological changes... and it has even been proposed that TB in older adults
should be considered as a different disease entity."
By and large, elderly patients feel less discomfort with tuberculosis than are younger patients. This changes dramatically as
soon as standard chemotherapy is initiated.
"According to our findings, there is an increasing risk of TB-drug adverse events when age increases. In previous reports, the occurrence
of any major side effect has been associated with age, especially amongst the elderly. The frequency of adverse reactions has
shown to increase in a progressive and direct form in relationship to age."
It appears that in elderly patients, the definite discomfort of the tuberculosis disease really sets in as soon as the treatment starts.
But it is safe to assume that public health institutions and physicians are more concerned about containing TB in communities
than the comfort of patients. Public health institutions advocate aggressive pharmacological treatment of tuberculosis in elderly patients
not because it would add to the quality of life of elderly patients but because elderly patients on a highly toxic drug cocktail are less
contagious. The elderly patient may suffer kidney or liver disease, be permanently nauseated, and even become deaf and blind because
of the treatment: the patient may suffer a plethora of other collateral damage, but at least in that condition,
he or she is less likely spread tuberculosis.
By Serge Kreutz, 2026
serge.kreutz@gmail.com
Updated July 10, 2024
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC3982203/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC8663960/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC6359177/
https://www.pnas.org/doi/10.1073/
pnas.1007967107
https://www.nature.com/
articles/s41579-022-00763-4
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC4663856/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC3346619/

https://www.niaid.nih.gov/
diseases-conditions/tbdrugs
https://reviews.webmd.com/drugs/
drugreview-1744
-rifampin-oral
or
https://www.drugs.com/comments/
rifampin/?search=&sort_reviews=
lowest_rating#reviews
https://reviews.webmd.com/
drugs/drugreview
-8665-isoniazid-oral
or
https://www.drugs.com/comments/
isoniazid/?search=&sort_reviews=
lowest_rating#reviews
https://pubmed.ncbi.nlm.nih.gov/30333388/
https://academic.oup.com/qjmed/
article/108/5/397/15430
https://bmcmedicine.biomedcentral.com/
articles/10.1186/
s12916-018-1033-7
https://bmcearnosethroatdisord.
biomedcentral.com/
articles/10.1186/1472-6815-7-5
https://www.sciencedirect.com/
science/article/
pii/S2405579421000188
https://www.rxlist.com/myambutol-drug.htm
https://www.mayoclinicproceedings.org/
article/S0025-6196(11)62721-3/fulltext
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC2647396/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC8779885/
fenton-reaction-AI.htm
https://www.nature.com/
articles/ncomms2898

https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC6568009/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC3676888/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC6722820/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC8615895/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC6359177/
https://www.nature.com/
articles/109663a0
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC6319124/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC10443783/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC4258661/
https://pubmed.ncbi.nlm.nih.gov/25790407/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC4937760/
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC3772817/
https://www.atsjournals.org/doi/full/
10.1164/rccm.201311-2043OE
https://globaltb.njms.rutgers.edu/
abouttb/historyoftb.php
journal.chestnet.org/
article/S0096-0217(15)30204-1/abstract
https://www.atsjournals.org/doi/full/
10.1164/rccm.200307-1016OE
https://www.atsjournals.org/doi/full/
10.1164/rccm.200307-1016OE
https://www.sciencedirect.com/topics/
immunology-and-microbiology/lung-gas-exchange

Mont Alto Sanatorium in Pennsylvania, USA
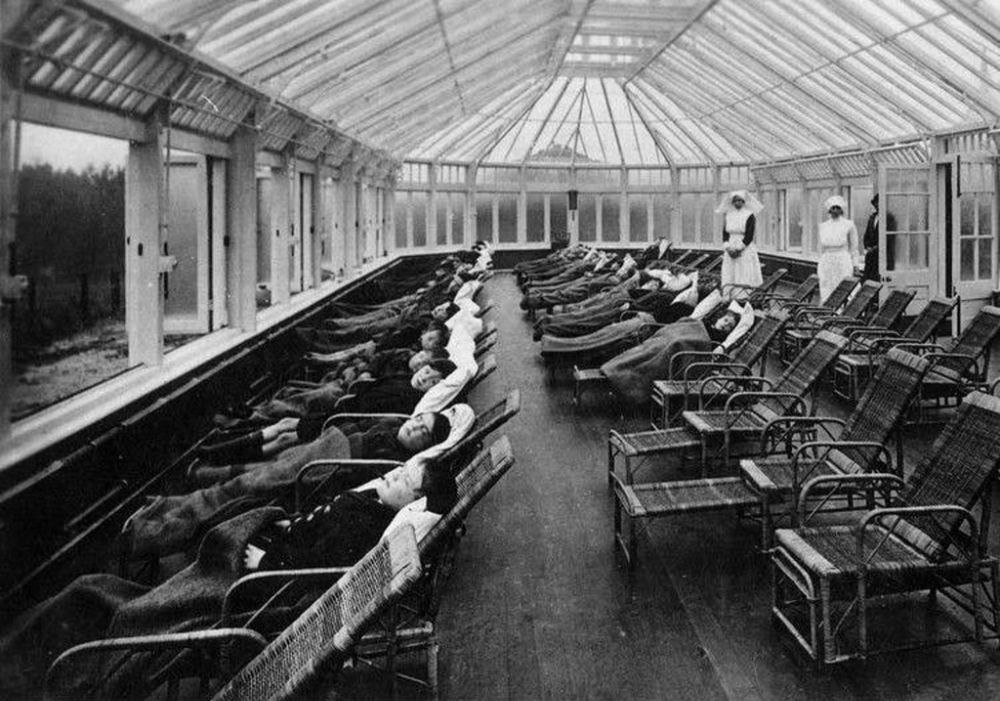
Stannington, UK, Children's Sanatorium, 1926
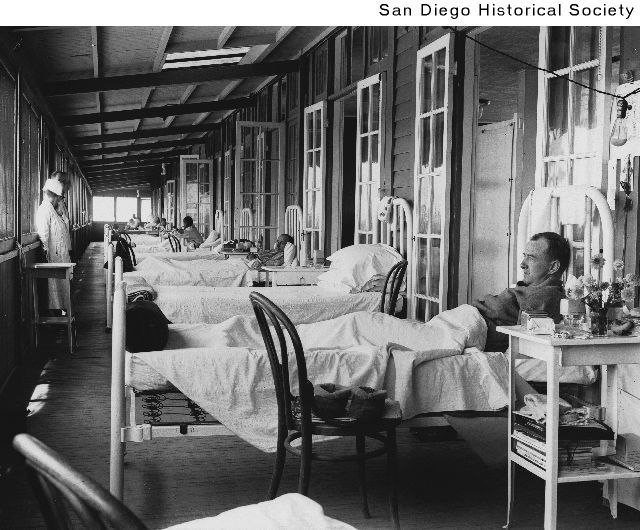
A ward at the Vauclain Tuberculosis Sanatorium, ca. 1920
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC8703289/
https://www.sciencedirect.com/science/
article/pii/S120197121401707X
https://openres.ersjournals.com/
content/erjor
/5/4/00228-2018.full.pdf
https://www.ncbi.nlm.nih.gov/pmc/
articles/PMC3217998/
